


Periodontal probes are the measuring instruments at the heart of every periodontal examination, used to record probing depths, attachment levels, recession and bleeding. They all look similar at a glance, but the marking pattern, tip shape and working-end design differ, and those differences affect how quickly and accurately you can chart. This guide explains the ten probes you are most likely to see, what their markings mean and where each one fits.
Key takeaways
- The marking pattern is the main difference between probes: some mark every millimeter, others use gaps or color bands.
- Gaps in markings (such as the missing 4 and 6 mm on a Williams probe) help prevent misreading.
- The WHO probe has a ball tip and targets screening rather than detailed charting.
- Nabers probes are curved for furcation assessment; plastic probes are often chosen for implants.
- Use one probe design consistently across your team for comparable records.

The top 10 periodontal probes
1. Williams probe
The Williams probe is one of the most recognized designs. It is marked at 1, 2, 3, 5, 7, 8, 9 and 10 mm, with the 4 and 6 mm marks deliberately missing. The gaps create visual reference points so readings are less likely to be confused.
Best for: general charting by clinicians who reading the gap pattern.
2. UNC-15 probe
The UNC-15 is a 15 mm probe marked at every millimeter, with dark color bands at the 5, 10 and 15 mm zones. The extra length makes it useful for deep pockets, and single-millimeter marks allow precise readings.
Best for: periodontal practices and anyone charting deep pockets or measuring clinical attachment levels.
3. Marquis color-coded probe
Marquis-style probes use alternating color bands in 3 mm segments, typically marked at 3, 6, 9 and 12 mm. The bold bands are fast to read under operatory light.
Best for: quick, efficient charting where readings are often rounded to the nearest band and then estimated within it.
4. Michigan O probe
The Michigan O has a thin, round working end with markings at 3, 6 and 8 mm. The slim tip slides into tight sulci comfortably.
Best for: clinicians who prefer a fine tip and minimal markings.
5. Michigan O with Williams markings
This hybrid combines the slim Michigan O tip with the Williams marking pattern (1, 2, 3, 5, 7, 8, 9 and 10 mm). It is a popular choice for teaching and general practice because it pairs a comfortable tip with familiar markings.
6. CP-12 probe
The CP-12 is marked at 3, 6, 9 and 12 mm, often with color banding. The design is similar in concept to the Marquis probe and gives clear landmarks for fast measurement.
Best for: routine recall charting where speed matters.
7. Goldman-Fox probe
The Goldman-Fox probe has a flattened rather than round working end, with Williams-style markings. Some clinicians find the flat blade easier to read and to position against the tooth.
8. WHO (CPI) probe
The WHO probe, used for the Community Periodontal Index, has a 0.5 mm ball tip and a color-coded band, commonly between 3.5 and 5.5 mm. Some versions have additional marks at 8.5 and 11.5 mm. The ball tip helps detect calculus and reduces the risk of over-penetration.
Best for: periodontal screening and epidemiological examinations rather than full six-point charting.
9. Nabers furcation probe
Nabers probes have a curved working end designed to enter and assess furcations on multi-rooted teeth. Many versions carry color bands, often at 3 mm intervals, to help estimate horizontal furcation involvement.
Best for: evaluating furcation involvement on maxillary and mandibular molars. A straight probe cannot reach into furcations effectively.
10. Plastic (implant) probe
Plastic or resin probes are flexible and non-metal, and many clinicians choose them for probing around dental implants. They are usually color-banded for easy reading.
Best for: implant maintenance visits and patients with sensitive tissue. Check the manufacturer’s instructions on whether the probe is reusable and how it should be reprocessed. Our list of implant maintenance instruments covers related tools.
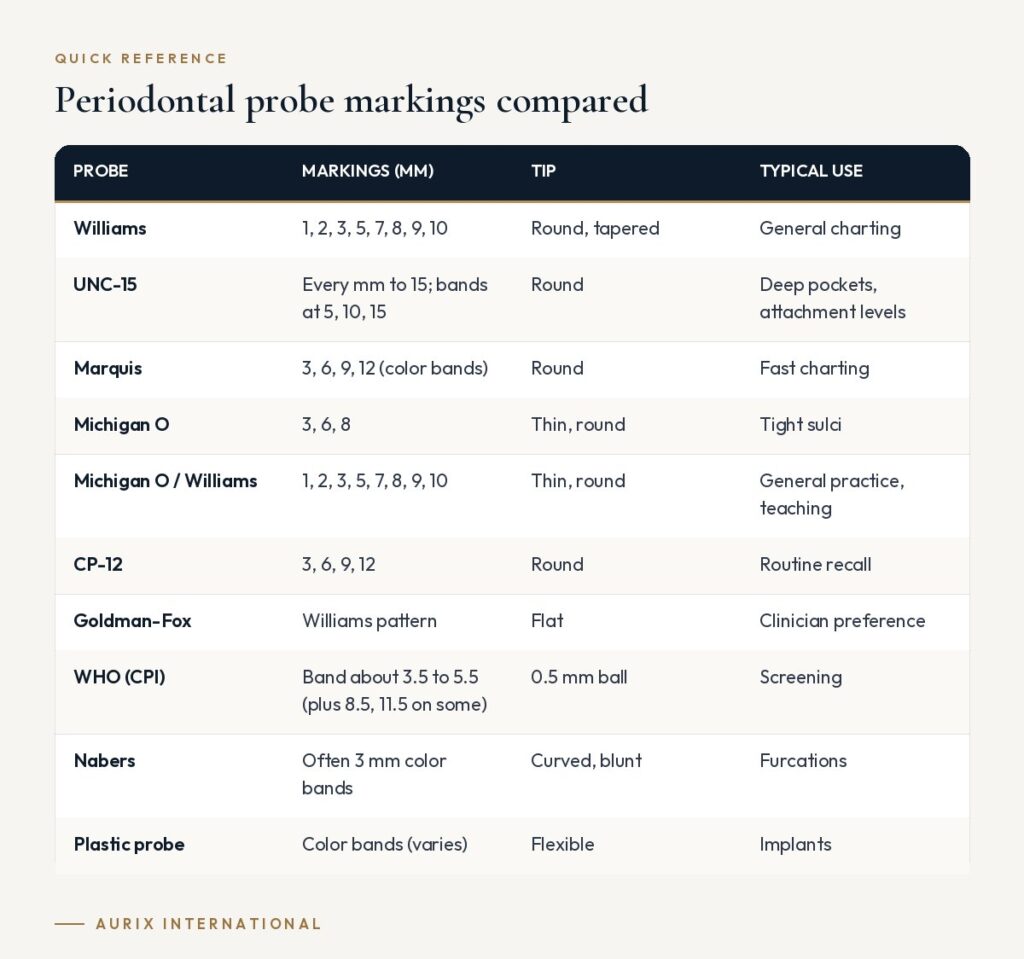
Periodontal probe markings compared
| Probe | Markings (mm) | Tip | Typical use |
|---|---|---|---|
| Williams | 1, 2, 3, 5, 7, 8, 9, 10 | Round, tapered | General charting |
| UNC-15 | Every mm to 15; bands at 5, 10, 15 | Round | Deep pockets, attachment levels |
| Marquis | 3, 6, 9, 12 (color bands) | Round | Fast charting |
| Michigan O | 3, 6, 8 | Thin, round | Tight sulci |
| Michigan O / Williams | 1, 2, 3, 5, 7, 8, 9, 10 | Thin, round | General practice, teaching |
| CP-12 | 3, 6, 9, 12 | Round | Routine recall |
| Goldman-Fox | Williams pattern | Flat | Clinician preference |
| WHO (CPI) | Band about 3.5 to 5.5 (plus 8.5, 11.5 on some) | 0.5 mm ball | Screening |
| Nabers | Often 3 mm color bands | Curved, blunt | Furcations |
| Plastic probe | Color bands (varies) | Flexible | Implants |
How to choose a periodontal probe
- Pick a marking system your team can read quickly. Color-banded probes are faster to read; single-millimeter probes are more precise. Choose one and use it consistently so records are comparable over time.
- Consider tip diameter. Thinner tips are more comfortable in tight tissue, but probing force should still be light. Many clinicians aim for a gentle, consistent pressure.
- Check marking durability. Laser-etched or deeply engraved markings resist fading through repeated sterilization better than printed ones. Inspect probes regularly and replace any with worn or illegible markings; see our monthly inspection checklist.
- Keep specialty probes on hand. A Nabers probe for furcations and a plastic probe for implants complement your main charting probe.
- Look at double-ended options. Probe/explorer combinations save cassette space. Our guide to periodontal probe markings has more detail on choosing.
Probing technique reminders
- Insert the probe gently, parallel to the long axis of the tooth.
- Walk the probe around the tooth in small steps rather than lifting it in and out.
- Angle slightly into interproximal areas so the tip reaches under the contact.
- Record six sites per tooth for a full periodontal chart, reading at the gingival margin.
- Note bleeding, suppuration and recession at the same time.
Frequently asked questions
Why does the Williams probe skip 4 and 6 mm?
The missing marks create visual landmarks. When the gingival margin sits in a gap, you can tell immediately whether the reading is 4 or 6 mm without counting every line.
Which probe is best for implants?
Many clinicians prefer plastic or other non-metal probes for implants because they are flexible. Follow the implant and probe manufacturers’ recommendations.
Can I use a WHO probe for full charting?
The WHO probe targets screening using the Community Periodontal Index. For detailed six-point charting, a probe with millimeter markings such as a UNC-15 or Williams is more practical.
How long do periodontal probes last?
Probes last until the markings fade, the tip bends or the instrument is damaged. Replace probes promptly when markings are no longer clearly legible, because inaccurate readings affect diagnosis.
Standardize your probes across every operatory. Aurix supplies periodontal probes and complete diagnostic sets in surgical-grade stainless steel, individually or in bulk. Request a probe quote →


